
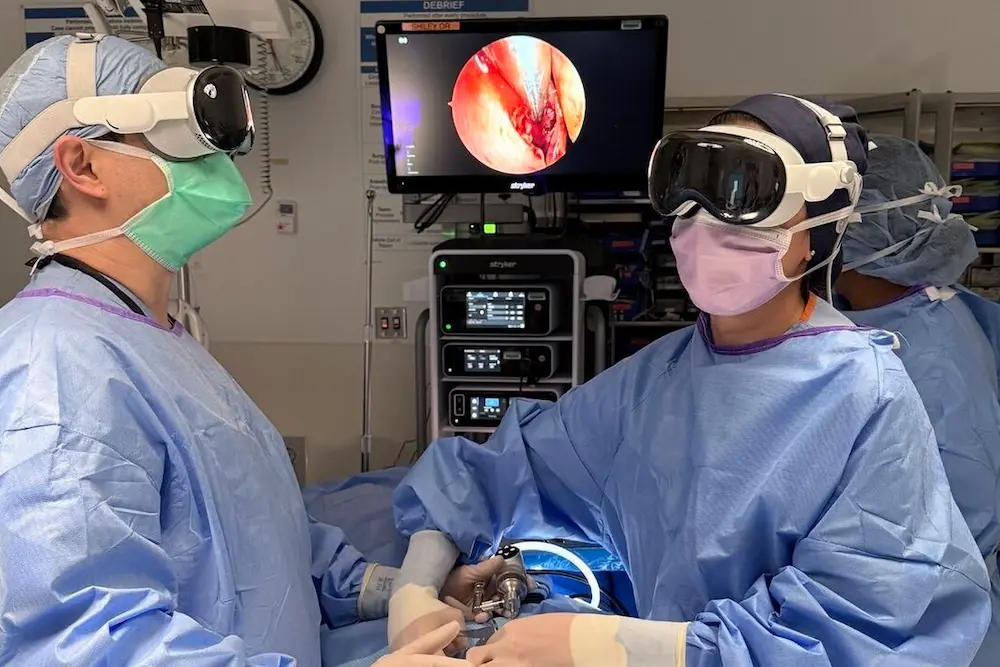
A 32-case UC San Diego comparison found procedures using Vision Pro as the primary display averaged 34.4 minutes, against 42.7 minutes with a conventional monitor. The single-centre, non-randomised study is preliminary.
Researchers at UC San Diego’s Shiley Eye Institute have reported shorter operating times and lower surgeon workload when Apple Vision Pro replaced a shared operating-room monitor during endoscopic tear-duct surgery.
The study in AJO International compared 16 procedures performed with Vision Pro against an equal-sized group using a conventional display. Mean operating time was 34.4 minutes with the headset and 42.7 minutes in the control group, a difference of 8.3 minutes or about 19%.
All 32 procedures achieved functional success, with no intraoperative or postoperative complications reported during follow-up of four to 12 months. Clinical outcomes were unchanged; the measured differences were in operating time and surgeon experience.
Eight Minutes Faster in a 32-Case Comparison
The researchers studied endoscopic dacryocystorhinostomy, or DCR, a procedure that creates a new drainage route for a blocked tear duct. Two fellows acted as the primary surgeons across the series, supported by three attending surgeons.
The operating-time difference was statistically significant (p=0.006). Surgeon responses also favoured the headset. Median overall workload on the NASA Task Load Index was 19.2 with Vision Pro and 40.0 with the conventional display (one-sided p=0.031). Physical demand showed the clearest reduction, and all five participating surgeons preferred the headset setup.
NASA-TLX is a self-reported measure, however, and only five surgeons contributed to the workload comparison. The preference and comfort results therefore describe a small group with direct experience of both arrangements rather than a representative surgical workforce.
Vision Pro Replaced a Shared Monitor
The headset was used as a wearable display for the live endoscopic image. It was not tested as an autonomous guidance system or as a source of 3D anatomical overlays.
In the control procedures, the operating and assisting surgeons shared a 32-inch 4K monitor positioned at the head of the table. Both had to rotate their upper bodies by about 90 degrees to see it. With Vision Pro, each surgeon could position a spatially anchored image in their own field of view while maintaining a forward-facing posture.
The existing endoscopy tower remained the video source. Its HDMI output was converted to NDI and streamed to both headsets over a secured, closed 5GHz Wi-Fi 6 network isolated from the institution’s other systems. Surgeons could resize and reposition the image using sterile hand gestures. They reported no perceptible latency, although the researchers did not measure latency objectively.
The change removed the need to share a fixed display and offered a plausible explanation for the lower physical workload. The study design cannot establish whether that change alone produced the shorter operating time. Differences in case complexity, surgeon familiarity or the order in which cases were performed could also have contributed.
Clinical Workflow is a Tough Test
Dr José Ferrer Costa previously told The XR Beat that healthcare XR should be close to “two clicks” from use with a patient. The UC San Diego team moved Vision Pro into 16 live procedures, although the paper does not establish a standard deployment model for other operating rooms.
Hospitals considering a similar setup would still need to document how staff launch and position the feed, clean and turn around the headsets, manage prescription inserts, support wireless connections and recover from a failed stream. Patient consent, local infection-control procedures, data handling and technical support also sit outside the 19% figure. Longer procedures need separate evidence on eye strain, fatigue, dry eye and headset comfort.
XRB’s enterprise lessons from AWE 2026 found that surgical XR still needs an internal owner, training, integration and performance evidence before a demonstration becomes routine work.
The Cost Comparison Covers Hardware, Not Deployment
The paper labels its cost work exploratory. Vision Pro received its video from the existing endoscopy tower, so the headset did not replace the tower, camera, light source or complete surgical visualisation stack.
Paper co-author Horace Dediu separately said Vision Pro represented less than 1% of the cost of conventional equipment and occupied less operating-room space. His summary of the study describes the headset as small and inexpensive in the context of an ophthalmology operating room.
The equipment comparison covers footprint and acquisition price rather than total deployment cost. Software, integration, device management, cleaning, accessories, support, training and replacement cycles can all affect the hospital cost. XRB’s look at Vision Pro’s place in the premium enterprise headset market shows why specialist buyers judge the hardware against the value of a defined workflow rather than consumer-headset pricing alone.
The authors reported no study funding and no conflicts relevant to the paper, while listing unrelated commercial relationships. No Apple funding or involvement was reported.
What Hospitals Can Take from the Study
Hospital XR teams now have a use case with measured operating time, workload and functional follow-up. It remains a prospective feasibility study of one procedure, at one centre, with 16 headset cases, no random assignment and no formal power calculation.
A larger multicentre trial would need to control for surgeon experience and case difficulty, measure setup and failure rates, and publish a fuller deployment cost. For now, Vision Pro has evidence as a personal surgical display in a specialised workflow. Hospitals still need local proof that the time saving survives everyday setup, cleaning, support and procurement.












